How to Choose the Best Distal Femoral Plate in 2026?

Choosing the best Distal Femoral Plate in 2026 requires more than comparing prices, brands, or polished product images. The right choice depends on fracture complexity, bone quality, soft-tissue condition, knee alignment, and the surgeon’s fixation strategy. A simple transverse fracture may need a different construct from a comminuted intra-articular injury. Patient-specific planning matters.

Orthopaedic trauma surgeon Dr. William M. Ricci has emphasized a practical treatment principle: “The goal is to restore alignment, promote union, and preserve function.” This principle remains relevant when evaluating a Distal Femoral Plate. Look for reliable distal fixation, appropriate screw options, sufficient contouring, and compatibility with minimally invasive techniques. The plate should support biological healing without unnecessarily disturbing local blood supply. It should also fit the patient’s anatomy, not merely match a catalogue photograph.

Clinical experience still exposes uncomfortable gaps. A stronger plate does not automatically produce a better result. Poor reduction, excessive stiffness, weak fixation in osteoporotic bone, or inadequate postoperative planning can compromise outcomes. No implant is perfect. That matters.

This guide examines the features that deserve careful attention in 2026, including locking technology, variable-angle fixation, plate length, material selection, imaging performance, and evidence from clinical practice. It also considers surgeon familiarity and manufacturer reliability, because small decisions during surgery can affect confidence, time, and recovery. The most suitable Distal Femoral Plate is not always the newest model. It is the system that matches the fracture, the patient, and the surgical reality.
How to Choose the Best Distal Femoral Plate in 2026?

Classify AO/OTA 33 Fractures and Quantify the 5–15% Nonunion Risk

Choosing the best distal femoral plate starts with accurate AO/OTA 33 fracture classification. Type 33-A fractures are extra-articular, while 33-B fractures involve part of the joint surface. Type 33-C fractures extend completely through the articular block. Each group demands different reduction and fixation priorities. Classification is not always tidy. A fracture may show metaphyseal comminution, coronal splits, and bone loss together.

The reported nonunion risk is commonly estimated at 5–15%. This figure is a planning range, not a guarantee. Risk increases with severe comminution, open injury, poor bone quality, infection, smoking, and inadequate medial support. A simple-looking radiograph can hide weak biology. That deserves caution. Surgeons should assess alignment, soft-tissue condition, fracture gap, and early healing on serial images. One operation cannot correct every biological problem.

Plate selection should match the fracture map, not only the implant shape. A long lateral locked plate may support distal fragments, but it cannot replace accurate articular reduction. In selected 33-C injuries, additional fixation may improve medial stability. Working length, screw density, and construct stiffness also matter. Too many screws can create an overly rigid construct. Too few may fail in osteoporotic bone. The difficult judgment is balancing stability with biology. Even experienced teams should revisit the plan when postoperative alignment or callus formation looks disappointing.

Match Plate Shape to Anatomy: 5–7 Distal Screws and Working Span

How to Choose the Best Distal Femoral Plate in 2026?

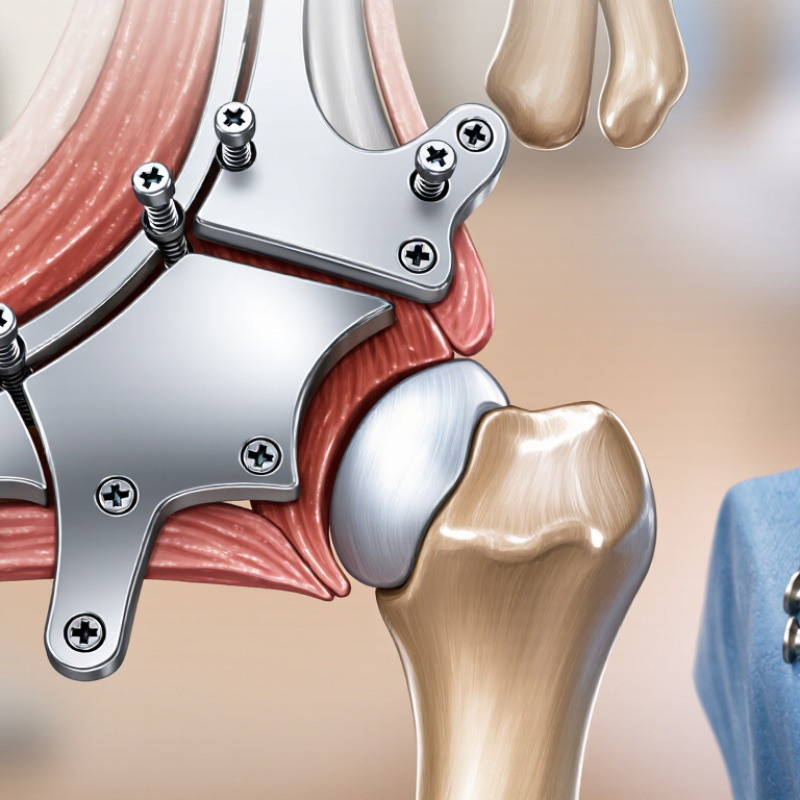
The right distal femoral plate should follow the patient’s anatomy, not force the bone into a flat shape. A plate with suitable distal flare can sit close to the condyles without excessive soft-tissue pressure. Check the anterior, lateral, and posterior contours before fixation. Small mismatches matter.

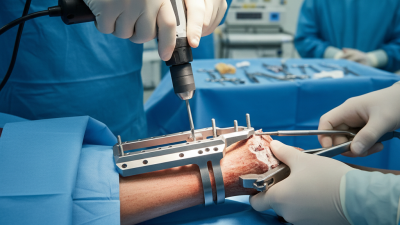
Aim for five to seven distal screws when the fracture pattern and bone stock permit. These screws should support the articular block while avoiding joint penetration. Their trajectories must be confirmed on multiple fluoroscopic views. More screws do not always mean better fixation. Poor placement can create stiffness, conflict, or unnecessary stress. The working span also deserves careful thought. A short span may concentrate strain near the fracture. A longer span can improve load distribution, but it may reduce construct stiffness. The ideal choice depends on fracture length, comminution, and bone quality.

Tips: Measure the distal segment before surgery. Compare the plate’s radius with the patient’s femur. Preserve a practical working span across the comminuted zone. Avoid filling every hole near the fracture. I have seen planning assumptions fail when the lateral cortex was less supportive than expected. Recheck alignment after temporary fixation, especially in osteoporotic bone. An experienced surgeon should adapt the construct to imaging, reduction quality, and intraoperative findings.

Compare Construct Strength Under ASTM F382 Bending and Fatigue Tests

How to Choose the Best Distal Femoral Plate in 2026?

A distal femoral plate should be judged by measured construct behavior, not appearance alone. ASTM F382 testing offers a structured way to compare metallic bone plates under controlled conditions. Bending tests examine stiffness, yield behavior, and ultimate failure strength. These values show how a plate responds when load increases around the distal femur.

Fatigue testing adds a more realistic challenge. Repeated loading can expose weak screw holes, transitions, or plate edges that remain hidden during a single bending test. Review the test span, loading direction, cycle count, and failure definition. Small changes in setup can alter the result.

Compare plates tested with similar fixtures and screw configurations. Otherwise, the numbers may look precise but remain difficult to interpret.

Look for stable performance across both tests. A very stiff construct is not automatically the best choice. Excessive rigidity may affect load sharing, while insufficient stiffness can permit unwanted motion. Clinical judgment still matters. Bone quality, fracture pattern, plate length, and screw placement influence performance. ASTM results describe laboratory behavior, not guaranteed patient outcomes. No test is perfect. I would also inspect failure photographs and raw fatigue data, when available. A reported average can hide meaningful variation between specimens. Ask whether the construct failed gradually or suddenly. That detail may matter more than one impressive headline value.

Adjust for Osteoporosis and Periprosthetic Fractures Using Clinical Data

How to Choose the Best Distal Femoral Plate in 2026?

Choosing a distal femoral plate requires more than measuring fracture length. Start with full-length radiographs and CT scans. Review bone quality, fracture lines, implant position, and soft-tissue condition. Osteoporotic bone often needs longer plates with greater proximal fixation. Locking screws can improve purchase, but they cannot replace accurate reduction.

Clinical data should guide, not dictate, the decision. Cohort studies commonly report higher fixation failure in severe osteoporosis, especially with short constructs and medial comminution. Consider screw density, plate span, and working length together. In fragile bone, avoid filling every hole near the fracture. A balanced construct may reduce stress concentration.

Periprosthetic fractures demand another level of planning. Check the existing femoral component, available bone, and any stem or cement. A plate must fit around the implant without weakening the remaining cortex. Some cases require variable-angle fixation, cerclage support, or a combined medial strategy. The surgeon should compare local registry data with personal outcomes, including nonunion and reoperation rates.

Small details matter. A thin lateral cortex can split during drilling. Fluoroscopy may look acceptable while rotation remains wrong. I have learned that elegant planning can still fail when intraoperative findings differ from the scan. Reassess fixation after loading the limb. The safest choice is the construct that matches the patient’s bone, fracture pattern, and rehabilitation demands.

Verify 2026 Compliance: FDA 510(k), CE MDR, ISO 13485, and Outcomes

How to Choose the Best Distal Femoral Plate in 2026?

Compliance must be verified before comparing plate shape, hole design, or locking options. FDA 510(k) clearance confirms substantial equivalence, not superior clinical performance. Check the exact device, indications, materials, and cleared configurations in the FDA 510(k) database. For Europe, confirm CE marking under the Medical Device Regulation, not only an older directive certificate. Transitional deadlines vary by device class and certification status. A valid ISO 13485 certificate supports quality management, but it does not replace regulatory approval. The ISO Survey 2023 recorded more than 30,000 ISO 13485 certificates worldwide, showing broad adoption but not equal manufacturing quality.

Tips: Request the 510(k) number, current CE certificate, declaration of conformity, ISO 13485 scope, and notified-body details. Match every document to the plate model.

Clinical outcomes deserve equal attention.

Published orthopedic reviews commonly report distal femoral fracture nonunion rates near 5–15%, with greater risk in open injuries, severe comminution, and poor biology. Ask for follow-up duration, revision rates, infection data, and patient numbers. A polished brochure is not evidence.

One practical concern is often missed: a plate may be cleared, yet its instructions may not support your planned construct. That gap deserves scrutiny. Surgeons should also review screw trajectory, working length, medial support, and compatibility with intraoperative imaging. Real-world data can be incomplete. That is uncomfortable, but it should be stated clearly.