What Are the Top Types of Joint Arthroplasty Procedures?
Joint arthroplasty replaces or resurfaces a damaged joint to reduce pain and improve movement. The main procedures involve the hip and knee, but surgeons also operate on shoulders, elbows, and ankles. Each joint has different demands. A hip must support body weight; a shoulder needs a wide range of motion.
Orthopedic surgeon and outcomes researcher Kevin J. Bozic has emphasized the importance of patient-centered outcomes. A concise paraphrase of that principle is: “A successful joint replacement should ease pain and help restore daily function.” This is a paraphrase, not a verified verbatim quotation. That distinction matters when discussing medical evidence.
This overview examines total hip and knee replacement, partial knee replacement, and shoulder arthroplasty. It also considers revision surgery, which may be needed when an earlier implant wears out, loosens, or becomes infected. The details matter: a partial knee replacement treats only the damaged compartment, while a total replacement addresses more of the joint. Recovery varies. A patient’s health, implant choice, and rehabilitation plan can all affect the result.
The categories are useful, but not perfect. Real treatment decisions depend on diagnosis, imaging, symptoms, and clinical judgment—not a title or procedure list alone. No implant lasts forever. Knowing the options can help patients ask clearer questions and discuss likely benefits, risks, and recovery with a qualified orthopedic specialist.
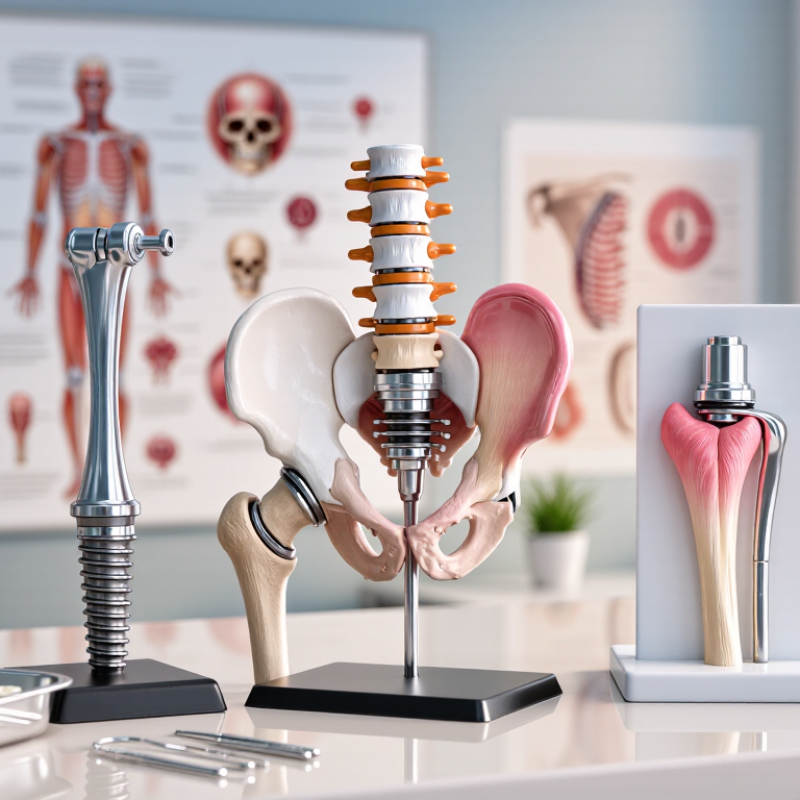
Table of Contents
[Hide]
Hip Arthroplasty: Total and Partial Hip Replacement
Hip arthroplasty replaces a damaged joint surface to relieve pain and improve movement. In a total hip replacement, surgeons replace both the femoral head and the socket, usually with implant components. A partial replacement, often called hemiarthroplasty, replaces the femoral head while leaving the natural socket in place. It is commonly considered for certain hip fractures, especially in older adults. The choice depends on fracture pattern, joint health, mobility, and overall medical fitness. Not interchangeable.
The distinction sounds tidy on paper. In practice, a person’s walking ability, pain, and recovery goals matter just as much. A CDC-supported U.S. analysis published in 2019 estimated that 2.5 million adults were living with total hip replacements. That figure describes people with total replacements, not annual operations or partial procedures. It helps show how common long-term recovery and follow-up are. Registry reports, including the National Joint Registry’s annual reports, also track implant outcomes and revisions, helping clinicians assess durability across patient groups. Still, population averages cannot predict one person’s result. Patients should ask what each option means for weight-bearing, rehabilitation, and likely movement after surgery. A slower recovery is possible. So is persistent stiffness, and that deserves an honest discussion before treatment.
What Are the Top Types of Joint Arthroplasty Procedures?
Hip Arthroplasty: Total and Partial Hip Replacement
Total hip replacement resurfaces both the femoral and acetabular sides of the joint. Partial hip replacement resurfaces the femoral side while leaving the acetabulum intact. The chart compares the number of native joint sides resurfaced.
Knee Arthroplasty: Total, Partial, and Revision Procedures
Knee arthroplasty replaces damaged joint surfaces when pain and stiffness limit daily life.
In total knee arthroplasty, surgeons resurface the thighbone and shinbone, and sometimes the kneecap. It is often considered when arthritis affects several parts of the knee.
A patient may notice the practical difference while climbing stairs or standing from a chair, though recovery varies.
Partial knee arthroplasty replaces only the damaged compartment. It may suit people whose arthritis is limited to one area and whose ligaments remain functional.
The incision and bone removal can be smaller, but this is not automatically the better option. Disease elsewhere in the knee may progress, and careful imaging and examination guide selection.
The American Joint Replacement Registry’s 2023 Annual Report analyzed more than 3.2 million hip and knee procedures reported from 2012 through 2022. That scale supports informed discussion, but registry averages cannot predict an individual result.
Revision knee arthroplasty replaces some or all components from an earlier operation. Surgeons may consider it for loosening, infection, instability, or worn parts.
It can require longer surgery and specialized components, especially when bone has been lost. The reasons matter.
A registry records patterns across patients, while a treatment decision must account for one person’s health, goals, and knee condition.
Even experienced teams face uncertainty.
Shoulder Arthroplasty: Anatomic and Reverse Replacements
Shoulder arthroplasty replaces damaged joint surfaces to ease pain and improve movement. The two main designs are anatomic and reverse replacements. They differ in how the joint is shaped and which muscles help move the arm. The choice depends on more than an X-ray.
An anatomic replacement keeps the shoulder’s natural arrangement: a rounded ball meets a socket. It is often considered when the rotator cuff, a group of tendons that helps control the arm, still works well. A surgeon may use imaging and examination findings to assess the cuff and socket. Recovery takes time.
A reverse replacement switches the ball and socket positions. This design allows the deltoid muscle to lift the arm when a severely damaged rotator cuff cannot do so effectively. It may be appropriate for some people with major cuff damage, but it is not automatically the better option. Real shoulders are less tidy than diagrams suggest. Bone quality, prior surgery, daily activities, and other health conditions can all matter. After either procedure, rehabilitation usually progresses gradually, with careful movement practice and limits on lifting. Stiffness, infection, or implant-related problems are possible, so expected benefits and risks should be discussed with an orthopedic surgeon.
Elbow Arthroplasty: Partial and Total Joint Replacement
Elbow arthroplasty replaces damaged joint surfaces to reduce pain and restore useful movement. A partial replacement, often called hemiarthroplasty, replaces one side of the joint. Surgeons may consider it for selected fractures when the opposing surface remains healthy. Total elbow arthroplasty replaces both sides, using components joined by a hinge or linked mechanism.
It may be considered for severe arthritis, complex fractures, or major joint damage. The choice depends on bone quality, ligaments, activity needs, and the cause of damage. The distinction is not always neat.
Registry evidence offers useful context, but not a personal forecast. An analysis using Norwegian Arthroplasty Register data reported approximately 81% implant survival at 10 years after total elbow replacement. Survival means the implant had not been revised; it does not guarantee a pain-free or unrestricted elbow.
Complications can include infection, loosening, instability, and nerve problems. These risks deserve a clear discussion before surgery. Afterward, rehabilitation often begins with careful guided movement, while lifting limits may protect the implant. Details vary by patient and surgeon.
A small, persistent ache can also be hard to interpret, so follow-up matters. The evidence base is smaller than for hip and knee replacement, and long-term results vary by diagnosis and implant type.
Ankle Arthroplasty: Total Ankle Replacement
Total ankle replacement (TAR) replaces worn ankle joint surfaces with artificial components, aiming to ease pain while preserving some up-and-down movement. It is commonly considered for severe ankle arthritis when symptoms remain limiting despite non-surgical care. The decision depends on more than an X-ray: bone quality, alignment, activity, and nearby joint health all matter. Small details matter. A visibly swollen ankle after a short walk, for example, may help a specialist understand how symptoms affect daily life.
The UK TARVA trial, reported by the National Institute for Health and Care Research, randomized 303 people at 17 hospitals to ankle replacement or fusion. At 52 weeks, both groups had improved, with no statistically significant overall difference in the main outcome. That is useful evidence, but one year cannot establish how long an implant will last. Recovery also varies: patients may use a boot or walking aids, and swelling can linger while strength and balance return. It is not a quick reset. Follow-up appointments and rehabilitation help clinicians monitor movement, wound healing, and changing pain; the best approach should be tailored to the individual.
| Dimension | Typical Information | Clinical Context |
|---|---|---|
| Procedure | Total ankle replacement, also called total ankle arthroplasty, replaces the damaged joint surfaces of the ankle with artificial components. | It is a surgical option for selected people with severe ankle joint disease when nonsurgical care has not provided adequate relief. |
| Common reason for surgery | End-stage ankle arthritis, including arthritis that develops after an injury, inflammatory arthritis, or wear-related joint damage. | Symptoms may include persistent pain, stiffness, swelling, and difficulty with walking or other weight-bearing activities. |
| Main components | A tibial component, a talar component, and a bearing surface between them. The bearing is commonly made of medical-grade polyethylene. | The components create new articulating surfaces while retaining movement at the ankle joint. |
| Primary goal | Reduce pain while preserving some up-and-down ankle motion. | The amount of motion restored varies. Replacement does not recreate a normal, disease-free ankle. |
| Possible alternative | Ankle fusion, also known as ankle arthrodesis, joins the bones of the ankle to reduce painful movement. | Fusion and replacement have different benefits and trade-offs. The appropriate option depends on the person’s condition, activity needs, and overall health. |
| Factors considered for candidacy | Joint damage, bone quality, ankle alignment and stability, circulation, skin condition, activity level, and general health. | Severe deformity, poor bone stock, active infection, or certain nerve and blood-flow problems may affect whether replacement is suitable. |
| Potential benefits | Pain relief and preservation of ankle motion compared with a procedure that permanently fuses the ankle joint. | Individual results vary, and some people continue to have pain, limited motion, or difficulty with particular activities. |
| Potential risks | Infection, wound-healing problems, blood clots, nerve or blood-vessel injury, persistent pain, component loosening or wear, and need for further surgery. | Risk depends on individual health and surgical factors. Ankle replacement components can wear or fail over time. |
| Recovery considerations | Recovery generally involves a period of protected weight-bearing, wound care, rehabilitation, and gradual return to activity. | Weight-bearing instructions and rehabilitation schedules vary. The treating surgical team determines the appropriate plan. |
| Long-term activity | Walking and lower-impact activities may be possible after recovery, depending on healing and function. | High-impact activities may increase stress on the implant; activity recommendations should be discussed with the surgeon. |
General educational information only. Suitability, expected outcomes, risks, and recovery plans should be assessed individually by a qualified foot and ankle specialist.
Related Posts
-
7 Best Knee Arthroscopy Surgery Suppliers for Global Buyers?
-
China Best Joint Arthroplasty Procedure Benefits and Considerations?
-
What is Maxillofacial Trauma Surgery and its Importance in Recovery?
-
2026 How to Prepare for Limb Lengthening Surgery Effectively?
-

How to Choose the Right Proximal Humeral Plate
-
10 Essential Tips for Choosing Bone Graft Substitutes for Successful Surgery?